
Author Archives: Stephen Huffman

CPR for Pregnant Women- Step-by-Step Guide to Safe Maternal Resuscitation

Maternal cardiac arrest is a rare but life-threatening emergency that requires immediate and specialized care. The incidence is approximately 1 in every 12,000 deliveries, according to the American Heart Association (AHA). While uncommon, this statistic highlights the critical need for healthcare providers and bystanders to be prepared. The most common causes include hemorrhage, cardiovascular disease, amniotic fluid embolism, sepsis, and anesthesia complications, as identified by Jeejeebhoy et al. (2015). Recognizing these risks early can help in both prevention and prompt intervention. Standard techniques must be adapted when performing CPR on a pregnant woman to account for physiological changes during pregnancy. These CPR modifications are essential to protecting both the mother and the fetus. Our article provides a clear, step-by-step approach to managing maternal cardiac arrest. This will help you respond effectively in this critical situation. Every second counts—being informed can save two lives, which is why building real hands-on confidence through SimpleCPR’s online certification courses matters as much as reading about it.

Standard techniques must be adapted when performing CPR on a pregnant woman to account for physiological changes during pregnancy. These CPR modifications are essential to protecting both the mother and the fetus. Our article provides a clear, step-by-step approach to managing maternal cardiac arrest. This will help you respond effectively in this critical situation. Every second counts—being informed can save two lives.

Why Pregnancy Requires Modified CPR?

Pregnancy introduces significant physiological changes that make standard CPR less effective. To improve outcomes, specific CPR modifications are necessary when responding to a maternal cardiac arrest — a topic covered in more depth in our guide to the vital pregnant woman CPR technique that could save two lives.

Aortocaval compression and reduced cardiac output

The enlarged uterus can compress the aorta and inferior vena cava when the woman lies flat on her back, in the advanced months of pregnancy. This is known as aortocaval compression, and it can reduce cardiac output by 30–40% during the third trimester, as per the American Heart Association (AHA). This drastic reduction impairs blood flow to both the mother and the fetus, making chest compressions less effective. To counter this, left uterine displacement (LUD)—manually or by tilting the patient 15 to 30 degrees to the left—is essential during CPR for a pregnant woman.

Time-sensitive delivery decisions

For pregnancies beyond 23–24 weeks of gestation, the AHA emphasizes that resuscitative hysterotomy (emergency C-section) within 5 minutes of arrest offers the best chance for neonatal survival. This timeline underscores the urgency of initiating advanced interventions without delay.

Understanding these physiological changes is critical for improving survival outcomes. Modifying standard CPR in pregnant women is not optional—it is vital for saving both maternal and fetal lives.

Precautions and Initial Assessment

When responding to a maternal cardiac arrest, early recognition and appropriate action are crucial. The unique pregnancy physiology—including increased blood volume, altered respiratory function, and risk of aortocaval compression—requires immediate assessment and specific precautions to optimize survival for both mother and fetus.

Check responsiveness and call for help.

Start by checking the woman’s responsiveness and breathing. If she is unresponsive and not breathing normally, call emergency services immediately. Be sure to state clearly that the patient is pregnant. This prompts dispatchers to notify the appropriate team and prepare for interventions like perimortem cesarean delivery.

Assess gestational age

Quickly assess whether the pregnancy is visibly ≥20 weeks of gestation, usually indicated by a uterus at or above the level of the umbilicus. If so, initiate left uterine displacement (LUD) to relieve aortocaval compression. This can be done manually or by placing a wedge or towel under the right hip to tilt the patient 15–30 degrees to the left.

Prepare for pregnancy-specific interventions.

Once cardiac arrest is confirmed, begin BLS in pregnancy with high-quality chest compressions and ensure airway management with minimal interruptions. Defibrillation in pregnancy should be administered as in non-pregnant patients—no modifications in energy levels are needed. However, all providers should be trained in ACLS in pregnancy, which includes early consideration of resuscitative hysterotomy if there is no return of spontaneous circulation within 4–5 minutes.

Positioning and Left Uterine Displacement (LUD)

Proper positioning during CPR for a pregnant woman is critical to prevent aortocaval compression, which can significantly reduce blood flow to vital organs and compromise resuscitation efforts. Understanding and applying left uterine displacement (LUD) can improve chest compressions and increase the chance of survival for both mother and baby.

Why is full side-lying contraindicated?

A common misconception is to place the pregnant woman in a full side-lying position to relieve aortocaval compression. However, this is not recommended during cardiac arrest. Full lateral positioning makes high-quality chest compressions nearly impossible due to instability and poor access to the chest. According to the BLS pregnancy and ACLS in pregnancy guidelines, chest compressions must be performed with the patient in a supine position while applying LUD.

How to perform left uterine displacement?

LUD can be done manually by standing on the patient’s left side and gently pushing the uterus to the left. Alternatively, place a firm wedge (such as a blanket or rolled towel) under the woman’s right hip to create a 15–30 degree tilt. The pressure on inferior vena cava and aorta get relieved, improving venous return and cardiac output.

Maintaining LUD throughout resuscitation is vital, especially when preparing for perimortem cesarean delivery. It supports circulation until either return of spontaneous circulation (ROSC) or resuscitative hysterotomy is performed. In cases of defibrillation in pregnancy, no changes in energy settings are needed, and shocks can be delivered safely with proper positioning.

Performing High-Quality Chest Compressions

Effective chest compressions are vital during pregnancy resuscitation to restore circulation. Due to changes in pregnancy physiology, such as an improved diaphragm, minor adjustments in technique are necessary.
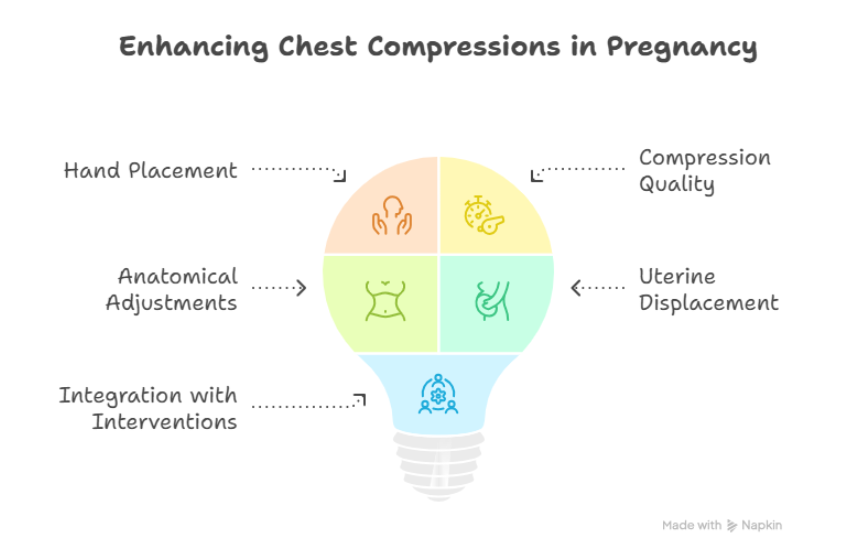
Performing High-Quality Chest Compressions

Hand placement and compression quality

Place your hands slightly higher on the sternum than usual. This accounts for the third shift of internal organs for a pregnant woman. Compressions should be delivered at 100–120 per minute with at least 2 inches (5 cm) depth — a technique that differs notably from infant chest compressions, which use a much lighter touch for a newborn’s smaller chest.

Adjusting for pregnancy anatomy

The growing uterus affects chest anatomy and diaphragm position. Proper hand placement helps ensure compressions generate adequate forward blood flow. Combine this with left uterine displacement to relieve aortocaval compression.

Integration with other interventions

Continue compressions while other team members prepare for airway management, defibrillation, or resuscitative hysterotomy if indicated. High-quality compressions are the foundation of all advanced measures, including targeted temperature management post-arrest.

Airway management and rescue breaths

Airway control is critical during pregnancy resuscitation, as pregnancy physiology increases oxygen demand and aspiration risk. Prompt, effective airway management supports both maternal and fetal survival.

Modified techniques for pregnant women

Use the head-tilt-chin-lift method cautiously, mindful of the increased soft tissue in the airway. If trauma is suspected, use the jaw-thrust maneuver. In maternal arrest, the risk of aspiration is high due to delayed gastric emptying and reduced esophageal tone.

Ventilation guidelines

Deliver rescue breaths with a bag-valve mask using 100% oxygen, at one breath every 6 seconds (10 breaths per minute), ensuring a visible chest rise. Avoid over-ventilation, which can decrease cardiac output. Secure the airway early with advanced techniques if trained personnel are available.

Role in overall resuscitation

Ventilation must occur with minimal interruption to compressions. Ensure left uterine displacement continues during ventilation. Efficient oxygenation reduces fetal hypoxia and supports targeted temperature management if spontaneous circulation is restored.

Defibrillation in pregnancy

Defibrillation pregnancy protocols follow the same principles as in non-pregnant patients, but must be executed without delay. Cardiac arrest rhythms such as ventricular fibrillation or pulseless ventricular tachycardia require immediate defibrillation.

Pad placement and safety

Place AED pads in the standard anterior-lateral positions. If the abdomen interferes, pads may be adjusted slightly to accommodate the body’s shape. Electrical shocks do not increase the risk to the fetus. Prioritize maternal survival, as restoring maternal circulation directly supports fetal life.

No delay in defibrillation

Do not delay defibrillation for fetal monitoring, oxygen delivery, or setup of other interventions. If a shockable rhythm is identified, deliver the shock at standard energy levels. Continue high-quality compressions and left uterine displacement immediately after each shock.

Integration with advanced care

If there’s no return of spontaneous circulation within 4–5 minutes and gestational age is ≥23–24 weeks, initiate resuscitative hysterotomy per current pregnancy resuscitation guidelines. Defibrillation should never be withheld or delayed when clinically indicated.

Quick, decisive action in defibrillation pregnancy scenarios is vital. Combined with quality CPR, airway management, and appropriate interventions, timely defibrillation can be life-saving in maternal arrest causes involving shockable rhythms.

Advanced Interventions and the 4-Minute Rule

In cases of maternal cardiac arrest, rapid escalation to advanced care is essential. The pregnant CPR protocol includes specific guidelines for timing, medication, and potential delivery decisions to maximize survival for both the mother and fetus.
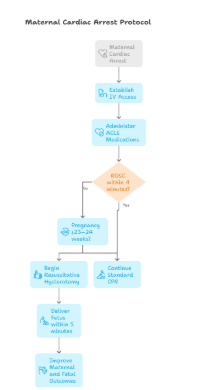
Advanced Interventions and the 4-Minute Rule

IV access and medication

Establish IV access above the diaphragm, typically in the upper extremities, to ensure adequate circulation during arrest. Administer ACLS medications as outlined by the American Heart Association (AHA), following standard dosing protocols. Medications should not be withheld due to pregnancy unless contraindicated.

The 4-minute rule and resuscitative hysterotomy

If there is no return of spontaneous circulation (ROSC) within 4 minutes, and the pregnancy is ≥23–24 weeks of gestation, begin resuscitative hysterotomy immediately. The goal is to deliver the fetus within 5 minutes to improve both maternal and fetal outcomes. This emergency perimortem cesarean delivery relieves aortocaval compression and can significantly improve the chance of successful maternal resuscitation.

Post-resuscitation care

After achieving spontaneous circulation (ROSC) return in a pregnant patient, careful post-resuscitation management is essential to stabilize both mother and fetus.

Targeted temperature management and monitoring

Initiate targeted temperature management (TTM) if indicated to preserve neurological function. TTM can be safely administered in pregnancy under expert guidance. Continuous fetal monitoring should begin as soon as the mother is stabilized to assess fetal well-being. This includes monitoring fetal heart rate, variability, and potential signs of distress.

Transfer and ongoing care

Transfer the mother to a tertiary care center with obstetric, neonatal, and intensive care resources. Close collaboration between critical care, obstetrics, and neonatology teams ensures comprehensive care. Maintain airway management in pregnancy and monitor for complications like bleeding, arrhythmias, or multi-organ dysfunction. Families preparing for a new arrival may also want to understand infant CPR and why you need to know how to do it, since newborns can face their own emergencies.

Post-resuscitation care must follow the pregnant CPR protocol and include follow-up assessments for both maternal and fetal health. It is insufficient to achieve ROSC—ongoing management is vital for full recovery.

Training and maintaining lifesaving skills

Proper response to maternal arrest depends on routine, high-quality training. CPR for pregnant women scenarios are rare, but the consequences of unpreparedness are severe.

Regular simulation drills

Conduct regular interdisciplinary drills that simulate pregnant CPR protocol situations. Teams should practice initiating chest compressions in pregnancy, performing airway management in pregnancy, applying left uterine displacement, and conducting resuscitative hysterotomy. These realistic scenarios help refine timing, coordination, and role clarity in high-stress events.

Staying current with guidelines

Healthcare providers must stay current on evolving AHA guidelines and pregnancy resuscitation best practices. Updates in drug use, defibrillation safety, and post-resuscitation care are essential for effective response. Regular continuing education and certification in ACLS in pregnancy and BLS for pregnant patients ensure readiness, and expectant parents or caregivers can complement this with a Pediatric CPR certification course to be ready for the newborn’s needs as well.

What does HCP stand for?

Understanding the term HCP is essential for anyone in or interacting with the medical field. If you’ve ever asked, “What does HCP stand for?”, the answer is simple: HCP stands for Healthcare Personnel. This term refers to all individuals delivering health services to patients, either directly or indirectly. Whether you’re a nurse, physician, paramedic, technician, or even administrative staff in a clinical setting, you fall under the category of Healthcare Personnel. The HCP meaning goes beyond just those who provide hands-on care—it also includes individuals who support care delivery through essential roles in healthcare environments. Understanding who qualifies as an HCP is vital for correctly applying workplace policies, safety protocols, and public health guidelines. This article will explain what HCP means and why it’s a critical classification in everyday healthcare operations and emergency response planning.

Style Snapshot

  • HCP stands for Healthcare Personnel — a broad term that includes everyone involved in delivering healthcare services, from doctors and nurses to pharmacists, therapists, and administrative staff. The term also appears in other industries, such as materials science (hexagonal close-packed) and cloud computing (HashiCorp Cloud Platform). Understanding its meaning in context ensures accurate communication, compliance, and collaboration.

HCP in Healthcare: Definition & Scope

Understanding the scope of Healthcare Personnel (HCP) helps clarify how healthcare systems function effectively. According to the CDC, HCP includes all individuals working in healthcare settings who have potential exposure to patients or infectious materials. This broad HCP definition includes those who deliver direct patient care and those who support healthcare services. With over 22 million people employed in U.S. healthcare, the sector is the nation’s largest employer, highlighting the massive scale of the healthcare workforce. Recognizing who qualifies as an HCP is essential for implementing health and safety regulations across various roles and settings.

Who qualifies as an HCP?

Knowing who falls under this category is essential when asking what HCP stands for. Healthcare Personnel include a wide range of roles. These individuals may have clinical, technical, or supportive responsibilities in healthcare environments.

Healthcare Personnel (HCPs) include many professionals who contribute to patient care and medical operations. Key groups include physicians and surgeons, registered nurses, nurse practitioners, and physician assistants (PAs) who provide direct clinical care. Therapists—such as physical, respiratory, occupational, and speech therapists—offer essential rehabilitative services. Pharmacists and pharmacy technicians ensure proper medication management, while medical and nursing assistants support daily patient care tasks. Dentists and dental hygienists focus on oral health. Laboratory and radiologic technologists handle diagnostics, and administrative and support staff maintain efficient healthcare operations. Together, they form the backbone of the healthcare workforce.

With approximately 817,920 physicians and surgeons in the U.S. as of May 2023, this group represents a significant segment of the broader HCP population.

Roles & responsibilities of HCPs

The HCP responsibilities span multiple care and support areas, ensuring the healthcare system remains functional and responsive. Preventive duties include administering vaccines, educating patients on health risks, and performing routine screenings. Curative tasks involve diagnosing illnesses, performing procedures, and managing treatment plans. Beyond clinical care, healthcare personnel are also expected to communicate, provide emotional support, and educate patients and their families about health.

Compliance is another key aspect of HCP roles. They must follow guidelines for infection control, patient confidentiality, documentation standards, and ethical medical practices. These responsibilities are critical for patient safety and public health, and staying certified through recognized programs — whether choosing the American Red Cross or American Heart Association for CPR training — helps HCPs meet these standards consistently. With over 22 million individuals in the healthcare workforce, each HCP must contribute to a consistent standard of care.

Understanding the HCP definition helps recognize the wide range of duties involved and supports better policy development, staffing strategies, and healthcare delivery outcomes.

HCP in Pharma: Engagement & Importance

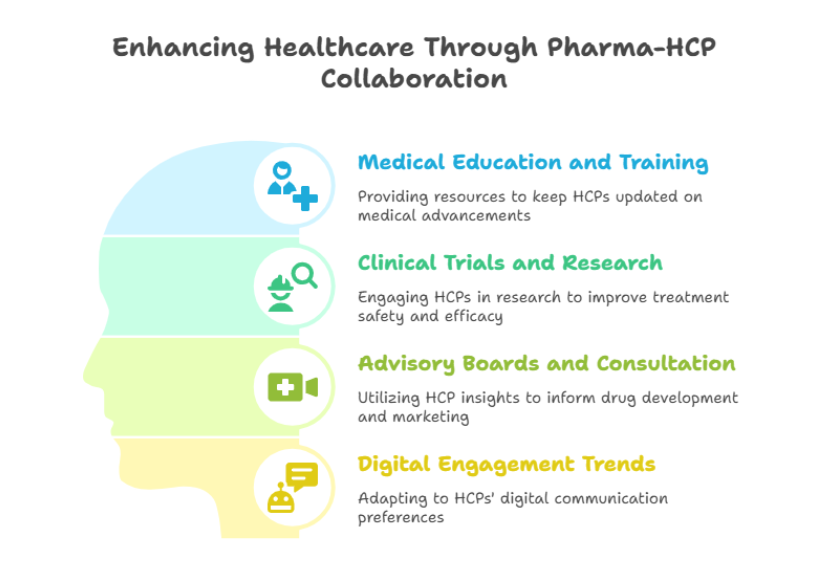
Pharmaceutical companies rely heavily on Healthcare Personnel (HCPs) to advance medical knowledge, ensure safe medication use, and improve patient outcomes. Understanding what HCPs stand for in this context is vital—they include physicians, pharmacists, nurse practitioners, and others who guide how medications are prescribed, dispensed, and monitored. Effective engagement between pharmaceutical companies and healthcare workers benefits clinical practice and public health.

Medical education and training

Pharma companies often provide educational resources to HCPs through continuing medical education (CME) programs, webinars, and scientific materials. These initiatives ensure that Healthcare Personnel stay current on drug indications, side effects, and evolving treatment protocols. In a rapidly changing medical landscape, this kind of support helps maintain high standards of care, much like understanding what CPR training involves helps HCPs stay prepared for life-threatening emergencies.

Clinical trials and research collaboration

Pharmaceutical firms also engage HCPs in clinical trials to learn about the safety and efficiency of new treatments. HCPs play critical roles as investigators, coordinators, and advisors. Their insights during trial design and implementation improve study relevance and patient outcomes. This partnership is essential to the development of evidence-based treatments.

Advisory boards and consultation

HCPs are frequently invited to join advisory boards or serve as consultants. Their frontline experience helps pharma companies know patient needs, treatment barriers, and clinical workflows. These collaborations influence drug development strategies and marketing practices while keeping them grounded in real-world care environments.

Digital engagement trends

With changing communication preferences, digital channels have become key to pharma-HCP interaction. As of 2022, 63% of physicians are considered “digital omnivores”, using multiple platforms such as email, webinars, and mobile apps—up from just 31% in 2019 (Indegene Digital Savvy HCP Survey). This shift underscores the need for versatile digital engagement strategies that align with modern HCP responsibilities and work environments.

Pharma-HCP collaboration continues to play a vital role in uplifting health outcomes and shaping the future of medicine.

HCP in Other Contexts

While the term HCP is widely recognized in the healthcare industry to describe professionals such as nurses, pharmacists, and therapists, it also appears in different fields with distinct meanings. Understanding these variations is essential to avoid confusion, especially in technical discussions. Whether you’re working in materials science, information technology, or recreational activities, the acronym HCP can take on new definitions. The following sections will examine how HCP is used beyond healthcare, including in engineering, cloud services, and everyday terminology.

Hexagonal close-packed (Materials Science)

In materials science, HCP stands for hexagonal close-packed, a typical arrangement of atoms in metallic crystals. This structure is one of the most efficient atomic packing arrangements, with a packing efficiency of about 74%. It describes how atoms are densely packed in a repeating hexagonal pattern, contributing to the strength and stability of certain metals. Examples of metals with an HCP structure include titanium, magnesium, and zinc. These materials often exhibit high strength and corrosion resistance, making them valuable in aerospace, medical devices, and industrial applications.

Understanding HCP structures is essential for materials engineers and researchers developing metal alloys for specialized use. While unrelated to nurses, pharmacists, or therapists, this version of HCP plays a crucial role in manufacturing and design technologies that sometimes benefit the healthcare industry, such as surgical tools and implantable devices.

HashiCorp Cloud Platform

In cloud computing, HCP refers to the HashiCorp Cloud Platform, a managed services suite that simplifies infrastructure deployment and security. HCP enables organizations to run popular tools like Vault, Consul, and Terraform in a fully managed cloud environment. These services support consistent infrastructure management, identity protection, and service networking across cloud platforms. The platform helps IT teams deploy and scale applications securely while reducing operational overhead. Although this form of HCP operates outside the traditional healthcare industry, healthcare organizations increasingly rely on cloud-based services for electronic health records, data storage, and compliance. For nurses, pharmacists, and therapists working in modern healthcare settings, this cloud infrastructure ensures they can access secure patient data and medical tools quickly and reliably. As digital transformation grows, the HashiCorp Cloud Platform supports the broader healthcare innovation ecosystem.

Other uses

HCP also appears in everyday terms outside science and technology. In the card game bridge, HCP stands for High Card Points, a scoring method used to evaluate a player’s hand strength based on the value of face cards. In golf, Handicap is sometimes shortened to HCP, referring to the numerical measure of a player’s potential ability, helping level the playing field between competitors of different skill levels. In Australia, the Home Care Package (HCP) is a government-subsidized program that provides long-term support to older individuals who wish to remain at home. It includes personal care, domestic assistance, and nursing support tailored to each person’s needs. While these uses are unrelated to pharmacists, therapists, or nurses directly, they reflect the diverse meanings the acronym HCP can hold. In particular, the Home Care Package system closely intersects with the healthcare industry, highlighting the importance of accurate interpretation based on context.

Why Understanding HCP Matters?

Recognizing the correct meaning of HCP is essential across various professional settings—especially in the healthcare industry, where nurses, pharmacists, therapists, and other professionals work in high-stakes environments. Understanding what HCP stands for ensures consistent communication, better coordination, and improved outcomes for healthcare providers and patients—and for those ready to build hands-on emergency response skills, you can compare our CPR certification course options to find the right fit for your role.

Improved communication and coordination

In the healthcare workforce, clarity around the HCP definition supports smoother communication among multidisciplinary teams. Whether between nurses, physicians, pharmacists, or therapists, understanding who qualifies as an HCP helps define roles, responsibilities, and expectations. This clarity minimizes confusion, especially when implementing protocols, distributing tasks, or coordinating care plans.

Better compliance and safety

Accurately identifying Healthcare Personnel is also essential for legal and regulatory compliance. Guidelines from the CDC, OSHA, and other agencies often apply specifically to HCPs. This includes training requirements, infection control protocols, and vaccination mandates, and knowing the difference between Heartsaver vs. BLS certification helps ensure HCPs get the right level of training for their role. Knowing who falls under this category ensures organizations meet compliance standards and keep their teams and patients safe.

Better patient outcomes

When HCP responsibilities are clearly defined, healthcare teams function more effectively. This leads to faster diagnosis, better medication management, and more accurate care delivery. For example, pharmacists can safely review prescriptions, therapists can focus on rehabilitation goals, and nurses can confidently monitor patient progress. The result is better patient care and improved outcomes.

Driving innovation and collaboration

A clear understanding of who HCPs are also helps industries beyond healthcare, including pharma and technology. Pharmaceutical companies engage HCPs for education, research, and clinical trials. Cloud services support HCPs with secure platforms for accessing data. When HCP roles are understood, these collaborations become more effective, fostering innovation that benefits patients and professionals.

Frequently Asked Questions

What is HCP in healthcare?

In healthcare, HCP stands for Healthcare Professional or Healthcare Personnel. It includes all paid or unpaid individuals who provide preventive, curative, or rehabilitative services. This term covers various roles such as physicians, nurses, therapists, pharmacists, EMTs, and social workers in the healthcare industry.

What does HCPs stand for in medical terms?

HCPs is the plural form of Healthcare Professionals. It refers to multiple individuals involved in patient care. It’s important not to confuse HCPs with HCPS, which stands for Hantavirus Cardiopulmonary Syndrome, a severe respiratory illness. The meaning depends on context, especially in medical communication.

Is a HCP a doctor?

A doctor is a type of HCP, but not all Healthcare Personnel are doctors. HCP is a broader term that includes nurses, pharmacists, therapists, physician assistants, dentists, and others involved in patient care within the healthcare workforce.

Further Resources & References

To better understand the role and responsibilities of healthcare personnel (HCPs), several trusted organizations and resources offer valuable guidance. Key industry bodies include the Centers for Disease Control and Prevention (CDC), which provides definitions and infection control protocols specific to HCPs. The World Health Organization (WHO) also outlines global standards for nurses, pharmacists, therapists, and other healthcare workforce members. Regulatory agencies like OSHA and The Joint Commission set compliance requirements to ensure safety in healthcare settings. Surveys such as the Indegene Digital Savvy HCP Survey 2022 and data from the U.S. Bureau of Labor Statistics offer insights into workforce trends and digital engagement.

For reliable, easy-to-understand content about CPR, healthcare practices, and public health education, Simple CPR is here to help. We encourage readers to check out our resources or share this post to support awareness and informed decision-making in the healthcare community.

CPR vs BLS: Understanding the Key Differences

Knowing how to differentiate between life and death in a medical emergency. Two commonly mentioned terms in emergency response training are CPR (Cardiopulmonary Resuscitation) and BLS (Basic Life Support). While often used interchangeably, they refer to different levels of training and care. Understanding the key differences between CPR and BLS is essential for healthcare professionals and the general public.

Style Snapshot

  • This article clarifies the distinctions between Cardiopulmonary Resuscitation (CPR) and Basic Life Support (BLS), emphasizing that while both are life-saving techniques, BLS encompasses CPR along with additional skills and tools tailored for healthcare professionals. Understanding these differences is crucial for selecting the appropriate training based on one’s role and responsibilities.

As per Sudden Cardiac Arrest Foundation, nearly 400,000 out-of-hospital heart attack happen annually in the U.S. This statistic underscores the prevalence of cardiac emergencies and the importance of being prepared. Whether you’re a bystander looking to assist or a medical professional delivering care, knowing when to apply CPR or BLS can save lives.

This article explains what sets CPR apart from BLS, who needs which training, and how each contributes to better emergency outcomes.

What is CPR?

Understanding CPR is the first step in recognizing how it differs from more advanced emergency care techniques like BLS. In the CPR vs BLS comparison, CPR refers to a foundational life-saving procedure anyone can learn and perform. While BLS includes CPR, the two serve different purposes depending on training level and situation. This section will help you understand the scope of cardiopulmonary resuscitation, when it should be used, and how it is performed.

Definition of CPR

Cardiopulmonary resuscitation (CPR) is done if a person’s heart stops beating or they stop breathing. It is a combination of chest compressions with rescue breaths that enable blood and oxygen circulating to vital organs. In the BLS versus CPR discussion, CPR is the core technique taught to laypersons and professionals. Learning CPR is critical because quick action can save lives. CPR statistics show its importance in increasing survival chances.

When to use CPR

CPR is performed if a person is unresponsive, not breathing, or only gasping. These situations often include drowning, sudden cardiac arrest, or choking. Lay rescuers are typically the first on scene, so knowing when to act is essential. In the CPR vs. BLS debate, most bystanders perform CPR before help arrives. Bystander CPR can double or triple survival chances—a powerful reason for the public to learn this vital skill.

Types of CPR

CPR includes chest compressions and rescue breaths (30:2 ratio), and hands-only CPR, which involves chest compressions only. Hands-only CPR is recommended for untrained bystanders. While both types are effective, choosing the right one depends on the rescuer’s training and comfort level. Many CPR myths suggest breaths aren’t needed, but conventional CPR remains essential for infants and children in respiratory arrest.

CPR steps for laypersons

Laypersons should follow the 30:2 compression-to-ventilation cycle — remembering what CAB stands for in CPR can help you recall the order: 30 chest compressions that get followed with two rescue breaths. Start by checking responsiveness and breathing, then call 911 or ask someone to do so. Start chest compressions strongly and fast in the center of the chest, followed by breaths if trained. Repeat the cycle until help arrives. Despite clear steps, “less than 20% of Americans are trained to perform CPR,” showing a significant gap in preparedness.

While CPR is widely taught to the general public, Basic Life Support (BLS) is designed for healthcare professionals and trained responders. In the CPR vs BLS comparison, BLS represents a more advanced and comprehensive skill set. It includes CPR as one of its elements but incorporates tools and techniques that improve patient outcomes. This section explains how BLS versus CPR training differs and what makes BLS essential in clinical and emergency settings.

Definition of BLS

Basic Life Support (BLS) refers to the level of medical care used to sustain life in emergencies until complete medical treatment can be given. It includes recognizing cardiac arrest, initiating high-quality CPR, and using equipment like an automated external defibrillator (AED). In the context of BLS versus CPR, BLS is more advanced and is part of professional emergency care. It equips responders to handle complex scenarios requiring quick, skilled intervention.

Components of BLS training

BLS components include several critical procedures: AED use, airway management, rescue breathing, and using a bag-valve-mask. These tools allow BLS providers to assist patients more effectively than CPR alone. Airway management and proper ventilation are emphasized, helping ensure oxygen delivery to the brain. The BLS provider course prepares professionals to perform these tasks confidently, often in high-pressure environments. These core components are what differentiate basic life support from layperson CPR.

BLS providers

BLS providers include healthcare workers such as nurses, EMTs, paramedics, doctors, and trained first responders. They are expected to perform CPR using advanced tools and techniques not typically used by the general public. In the CPR vs. BLS framework, BLS providers have the training to manage more complex emergencies.

Certification names

Two leading organizations offer basic life support certification: the American Heart Association’s AHA BLS Provider and the Red Cross BLS certification. While both cover similar content, they may differ in teaching format and assessment methods. Both are widely recognized in healthcare settings and meet professional training requirements. Anyone pursuing a BLS provider course should ensure the certification aligns with workplace needs and regulatory standards — and if you’re weighing options, see Heartsaver vs. BLS: Which CPR Certification Is Right for You.

Although CPR and BLS share a common goal—saving lives during cardiac and respiratory emergencies—they are not identical. Understanding the difference between BLS and CPR is essential when choosing the proper training for your role or responsibilities. Questions like “Is CPR certification the same as BLS?” or “Is BLS the same as CPR?” often arise. This section breaks down the distinctions in audience, techniques, equipment, and protocols to clarify the comparison between CPR and BLS.

Primary audience

CPR is designed for the general public, including teachers, coaches, and family members who may witness a sudden emergency. In contrast, BLS is intended for trained healthcare professionals. In the BLS versus CPR comparison, audience differences are apparent: BLS requires a higher medical understanding. Whether you’re comparing ACLS vs BLS or PALS vs BLS, each builds on BLS fundamentals tailored to specific populations or roles.

Scope of training & techniques

CPR training focuses on basic lifesaving actions such as chest compressions and rescue breaths, typically for a single-rescuer situation. BLS goes further, training responders for team-based care, coordinated roles, and advanced decision-making. This difference between BLS and CPR makes BLS better suited for hospital or emergency response environments. If you’re considering training options, the scope of CPR vs BLS can help guide your decision based on your responsibilities.

Equipment & airway management

In standard CPR courses, laypersons learn to use an AED (automated external defibrillator) and perform mouth-to-mouth breaths. BLS includes this but adds tools like the bag-valve-mask (BVM) and advanced airway devices. These additions enable more effective oxygenation and ventilation. The difference between BLS and CPR is clear in clinical settings where equipment plays a crucial role. For professionals, BLS bridges the gap between CPR and more advanced care like ACLS.

Assessment protocols

CPR emphasizes checking for responsiveness and normal breathing. BLS, however, includes more detailed assessments such as checking for a carotid pulse, monitoring vital signs, and using structured protocols to determine the next steps. This reflects a deeper understanding of patient conditions and clinical decision-making. When asking, “Is CPR certification the same as BLS?” remember that BLS training covers far more than just basic assessments—another reason it’s essential for medical personnel.

Similarities Between CPR and BLS

Despite their differences, CPR and BLS share many significant similarities. Both are designed to save lives by responding quickly and effectively during emergencies. The core procedures in each—chest compressions, rescue breathing, and use of an AED—are based on the same evidence-based guidelines from the American Heart Association (AHA). Whether performed by a layperson or a trained medical professional, the goal is to restore circulation and breathing as soon as possible.

Another key similarity is the emphasis on the Chain of Survival, which outlines the steps needed to improve survival rates after cardiac arrest. These include early recognition, immediate CPR, rapid defibrillation, effective advanced care, and post-resuscitation support. Both CPR and BLS stress the importance of each link in this chain.

Furthermore, both training programs work to correct CPR myths, such as the idea that mouth-to-mouth is always required or that you could harm someone by doing CPR incorrectly. Both certifications also teach the importance of scene safety, activating emergency services, and staying calm under pressure.

In short, while CPR vs BLS training may differ in complexity, they are united by the same life-saving mission and standardized practices vital in any emergency.

Recertification requirements for CPR and BLS

Both CPR and BLS certifications come with expiration dates, emphasizing the need for regular renewal to maintain readiness and confidence. For most providers, CPR certification is valid for two years, and recertification involves taking a refresher course or a whole class, depending on the certifying organization’s policies. This ensures that rescuers stay up to date with current CPR statistics and updated guidelines.

BLS certification also typically remains valid for two years, but may have stricter recertification requirements, especially in medical and clinical settings. To renew BLS, participants must complete a BLS provider course or a recognized refresher program. Healthcare facilities often require BLS certification to be current and may not accept expired credentials, highlighting the importance of timely renewal.

Recertification also reminds us that protocols and best practices can change. With advancements in resuscitation science, organizations like the AHA and Red Cross BLS programs periodically update CPR and BLS guidelines.

In both cases, continuing education plays a crucial role. Whether you’re a layperson or a professional, staying certified keeps your skills sharp and ensures you’re ready to act when every second counts.

Choosing the proper certification: CPR vs BLS

When deciding between CPR vs BLS certification, compare our CPR certification course options alongside your career path, job requirements, and personal readiness to guide your choice.

On the other hand, if you’re entering or already working in healthcare—as a nurse, EMT, or hospital technician—you’ll need Basic Life Support (BLS) certification. The BLS provider course goes beyond standard CPR by teaching team-based response strategies, airway management, and advanced equipment use. BLS is a job requirement in many clinical environments and is the foundation for further training, like ACLS vs BLS or PALS vs BLS certifications.

It’s also important to consider how comfortable you feel in emergencies. BLS offers more comprehensive instruction if you’re confident and want to deepen your skills. When comparing BLS versus CPR, the key is choosing the certification which is best suited for your role and the level of responsibility you’re prepared to take on during a crisis.

Beyond BLS: Advanced Life Support Certifications

Once you’ve mastered the fundamentals of CPR and BLS, advanced certifications are available for healthcare professionals who need to manage more complex emergencies. These courses help with learning Basic Life Support (BLS) and focus on specialized care in critical situations. Suppose you’re comparing ACLS vs BLS or PALS vs BLS. In that case, it’s essential to understand that advanced certifications are designed for professionals involved in direct patient care in hospitals or emergency settings. They require a solid foundation in BLS and clinical decision-making.

ACLS (Advanced Cardiovascular Life Support)

Advanced Cardiovascular Life Support (ACLS) training program is for healthcare professionals who handle cardiac and respiratory emergencies in adults. It covers advanced airway management, reading electrocardiograms (ECGs), and administering emergency medications. Unlike BLS, which focuses on immediate response, ACLS emphasizes diagnosis, treatment protocols, and team dynamics in critical care. This certification is required for paramedics, physicians, and ICU nurses. ACLS vs BLS highlights the move from basic response to clinical decision-making and leadership in resuscitation efforts, making it essential for those working in emergency departments or critical care units.

PALS (Pediatric Advanced Life Support)

Pediatric Advanced Life Support (PALS) focuses on emergency care for infants and children. It is designed for pediatricians, emergency nurses, and other healthcare providers who treat young patients. PALS training includes pediatric assessment, airway and breathing support, rhythm recognition, and managing shock and cardiac arrest in children. This course builds on BLS by addressing the unique needs of pediatric patients. In the PALS vs BLS comparison, PALS offers more specialized training and is often required in pediatric intensive care units and emergency settings where timely, child-specific care is essential.

Wrapping up

Understanding the difference between CPR and BLS is crucial when choosing the proper life-saving certification. While CPR equips laypersons to respond effectively in emergencies, BLS is designed for professionals who require advanced training and teamwork skills. Both play a vital role in improving survival outcomes during cardiac events. Whether you need CPR for basic preparedness or BLS for a healthcare role, timely training can save lives.

Take the first step today—enroll in SimpleCPR online certification to get certified or renew your credentials. Be prepared, stay confident, and help make a life-saving difference in your community.
